

A hair graft and a hair are different units. A graft is a small piece of tissue containing one or more hair follicles. A hair count describes individual hairs. Before comparing two transplant estimates, check which unit each number represents.
That distinction matters because a headline number does not explain where the grafts will be placed, what the donor area can provide or what result is realistic. An estimate becomes useful when a clinician connects the count to an individual plan.
What the terms mean
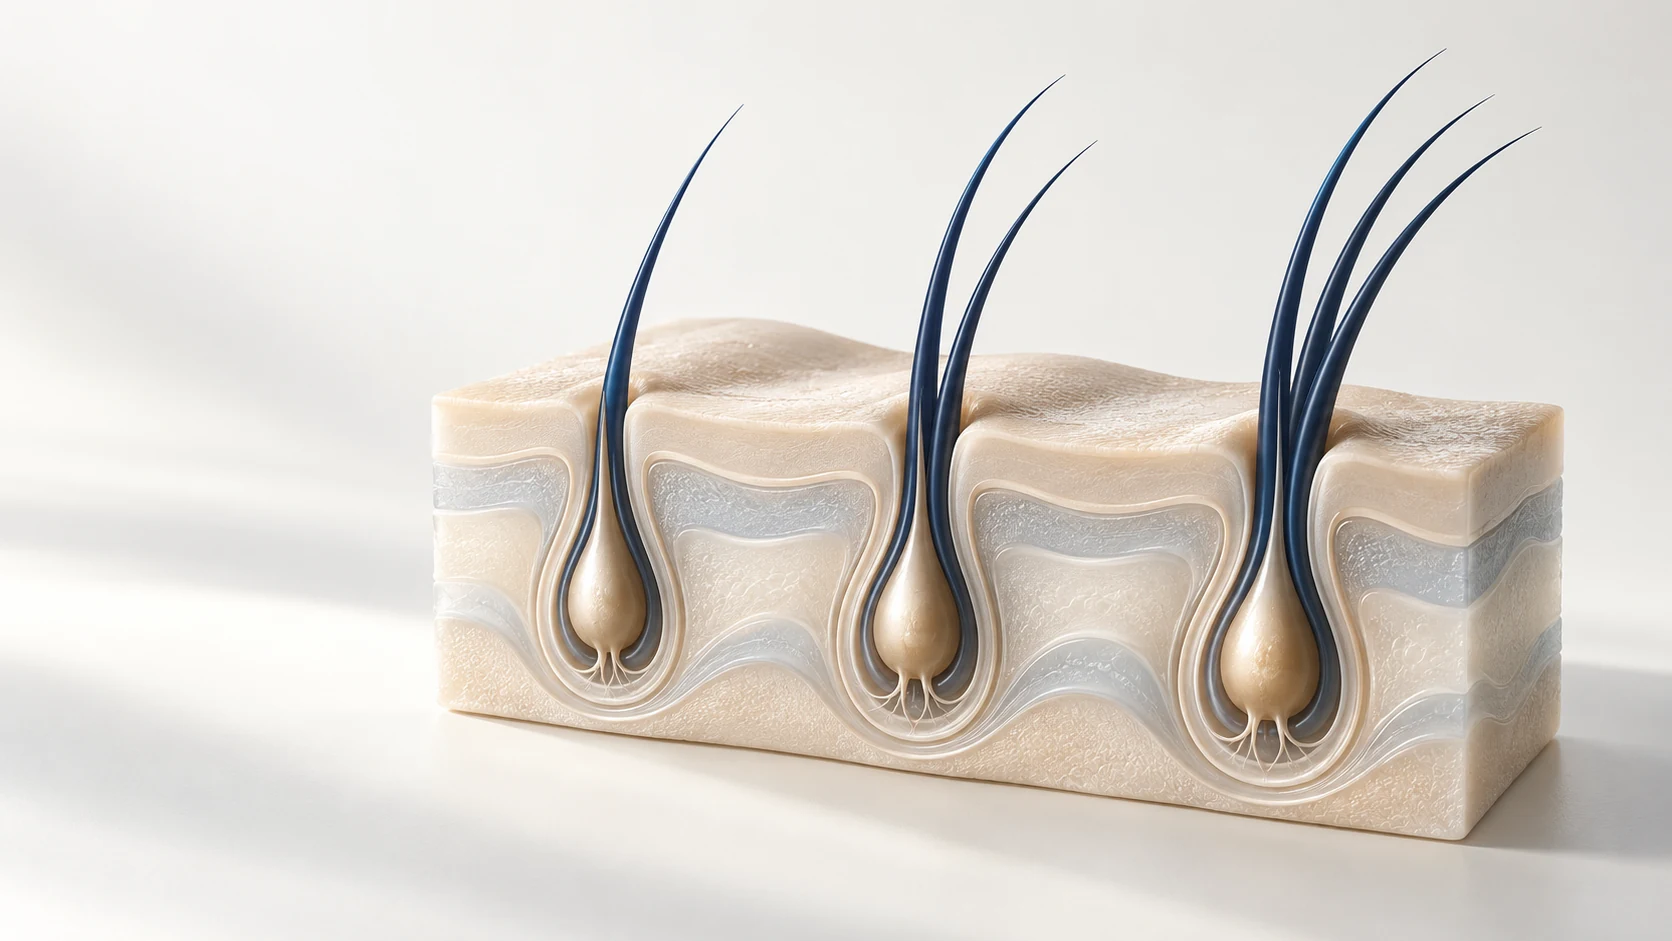
A hair follicle is the structure in the skin that produces a hair. The visible hair shaft is the part you see above the skin. Follicles can grow in naturally occurring groups, known as follicular units.
In a hair transplant, a graft contains follicles together with surrounding tissue. A follicular-unit graft may contain a single follicle or several. This is why the words ‘graft’, ‘follicle’ and ‘hair’ should not be used interchangeably when explaining a number.
The donor area supplies the grafts. The recipient area is where they are placed. These terms describe the two areas involved in the procedure; they do not tell you how many grafts should be moved.
Why there is no fixed conversion from grafts to hairs
A fixed multiplier cannot tell you the hair count in every transplant. Grafts do not all have the same composition, and an estimate may not yet include a detailed breakdown.
If a clinic gives you both figures, ask how the hair total was calculated. Is it a preliminary estimate, a calculation based on an assumed average or a count recorded during the procedure? Those descriptions mean different things. A clearly labelled estimate can be useful, but it should not look like a measurement that has already been made.
Similarly, the number of grafts planned or placed is not a guarantee of the number of hairs that will eventually grow. Ask the clinician to explain the limitations of the proposed result rather than treating the count as a promise.
Why more grafts do not answer every question
A larger figure may sound more comprehensive, but it is incomplete without a description of the treatment area. Ask which areas are being prioritised and which will remain untreated. A plan focused on the front of the scalp is not directly comparable with a plan that also addresses a wider area.
Hair characteristics and the available donor supply also matter. The same numerical target should not be assumed to produce the same appearance in different people. Donor-area planning helps explain why a proposed number needs to be considered alongside the hair being left behind.
An appropriate discussion therefore starts with your goals and clinical assessment. It should not start with a promise to reach the largest possible advertised count.
Read the estimate in five steps
1. Identify the unit. Ask whether every figure refers to grafts, follicles or hairs. If a brochure and a written plan use different terms, ask for a single clear explanation. An ‘up to’ figure in a package may describe a ceiling rather than an agreed clinical target; ask which it means.
2. Establish the stage of assessment. Who prepared the estimate, and what information did they use? Ask what still needs to be checked in person. A number supplied during an initial enquiry should be distinguished from the clinician’s plan after examination.
3. Connect the count to the area. Ask the clinician to show which parts of the scalp the proposed treatment covers. What is the intended priority? What degree of coverage or density would be unrealistic? Make sure the explanation describes your plan rather than another patient’s photographs.
4. Ask what could change. Find out which findings might lead the clinician to revise the estimate, reduce the planned treatment or recommend postponement. Ask how a changed recommendation would be explained before you decide whether to proceed.
5. Clarify the record. Ask whether you will receive a written summary of the agreed plan and a record of what was carried out. If planned and recorded counts differ, ask how the difference will be explained. The provider should clarify its own counting and documentation practices.
Comparing two estimates
Put the two explanations side by side before comparing the headline numbers. Do they use the same units? Do they cover the same areas? Were they prepared at the same stage of assessment? Do they describe similar priorities and limitations?
If one estimate contains much less detail, ask for clarification rather than filling in the gaps yourself. A difference in numbers may reflect different plans or assumptions. It does not, by itself, establish which recommendation is appropriate.
Keep the clinical plan and the financial terms clear. If the quotation uses a count to calculate a charge, ask the provider to explain that wording separately. A general guide cannot establish a clinic’s pricing or billing policy.
Frequently asked questions
Does one graft equal one hair?
Not necessarily. A graft can contain one or more hair follicles. Check whether the stated number is a graft count or a hair count before using it to compare plans.
Can I calculate my graft requirement from photographs?
Photographs may help an initial discussion, but they do not provide every part of a clinical assessment. Ask what examination and other information the clinician needs before confirming a recommendation.
Is a lower graft estimate always a less complete treatment?
No. You need to know what the plan is intended to address and why that approach was recommended. A count cannot explain suitability, donor limitations or the quality of a proposed plan on its own.
What should I do if the terminology is still unclear?
Ask the clinician to explain the estimate in plain language and record the unit next to each number. You should be able to describe what is proposed without having to guess what ‘grafts’ or ‘hairs’ means in the quotation.
A worked example for reading the units
Suppose an estimate lists 1,000 grafts and explains that some contain one follicle while others contain two or more. The graft figure alone does not tell you the total number of follicles. To calculate that total, you would need a reliable breakdown of how many grafts were counted in each group. Multiplying by an assumed average produces an estimate, not an independently measured result.
For illustration only, 500 one-follicle grafts and 500 two-follicle grafts would add up to 1,000 grafts containing 1,500 follicles. This is arithmetic, not a typical graft distribution, a recommended procedure size or a promise of eventual growth. The example shows why two equal graft totals can represent different underlying hair counts.
Ask the provider to distinguish the number discussed before surgery from the number documented afterwards. If a record uses the word “hair” where the quotation used “graft”, request clarification rather than trying to reconcile it with a universal conversion factor. Keep the original documents together so the clinician can explain which figures describe planning and which describe what was recorded during treatment.
Read the financial wording separately from the clinical count
A package described as including “up to” a number needs a separate explanation of both treatment scope and payment terms. Does the figure represent a maximum advertised allowance, a provisional clinical target or a billing unit? Ask what happens if the examination supports a smaller procedure, and what information you will receive before deciding whether to continue.
A useful quote makes it possible to understand the charge without interpreting medical terminology yourself. If payment is linked to a count, ask which count is used, how it is documented and whether the final amount can change. These are questions for the provider’s written terms; the example above does not establish any clinic’s pricing method.
For an international visit to Istanbul, settle these distinctions before buying non-refundable travel. You should not have to resolve a disagreement about units while simultaneously deciding whether to accept a changed surgical plan. A clear written explanation gives you something specific to review with the clinician and the administrative team, each within their own role.
Your next step
Take the estimate to a clinical consultation and ask the clinician to connect each number to the intended treatment area, donor assessment and limitations.
For the wider context, read hair transplantation explained.